
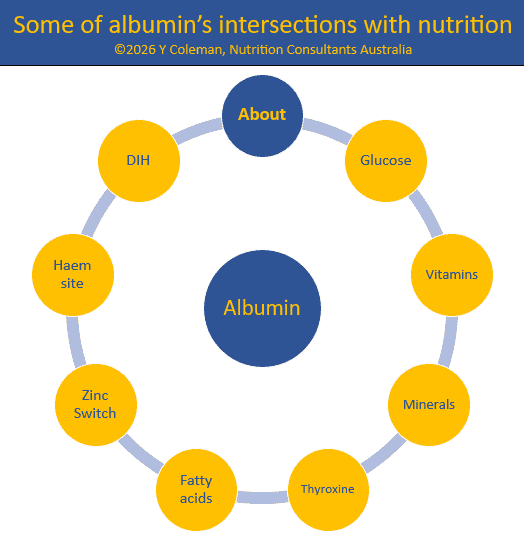
Albumin aka Human Serum Albumin (HSA) is the main protein in the blood.
Takeaways
Albumin is the primary protein in the blood plasma and is a primary indicator of several factors including nutritional status.
Albumin is the key carrier of many compounds, including many vitamins and minerals.
A Brief Overview
Albumin is part of a superfamily that includes vitamin D-binding protein (VDP), alpha-fetoprotein and alpha-albumin (afamin). The article Defining albumin as a glycoprotein with multiple N-linked glycosylation sites (DOI https://doi.org/10.1186/s12967-024-05000-5) has also identified albumin as a glycoprotein.
Because albumin is their primary distribution carrier, how compounds interact with albumin determines compound half-life, absorption, distribution, metabolism, and excretion.
Both albumin and the membrane transporters are commonly referred to as transporters. To minimise confusion, I shall refer to blood-specific distribution vehicles as carriers.
Albumin's Functions
Albumin’s range of functions is extensive and includes -
In some disease states, albumin can -
- be reduced in quantity and quality. The concept of ‘effective albumin concentration” refers to the amount of albumin that is structurally and functionally intact;
- have normal quantity, and altered function;
- be sufficiently modified that its binding properties and function are significantly affected to alter physiological responses.
Albumin's Synthesis
Albumin’s key statistics –
- typically takes about 15-30 minutes to produce,
- rate of synthesis that depends on amino acid supply, especially tryptophan, and is also affected by nutritional status and oncotic pressure,
- circulatory half-life is 16 hours,
- continuous secretion into the bloodstream,
- healthy adults produce 10–15 g of albumin per day,
- typical healthy adult range is 35‑50 g/L.
Hypoalbuminaemia
Hypoalbuminaemia occurs when there is both reduced synthesis and increased catabolism.
Factors causing hypoalbuminaemia include fasting, poor nutritional status, high osmotic pressure, and inflammation eg tumor necrosis factor α (TNFα), interleukin‑6 (IL-6).
Albumin's Structure
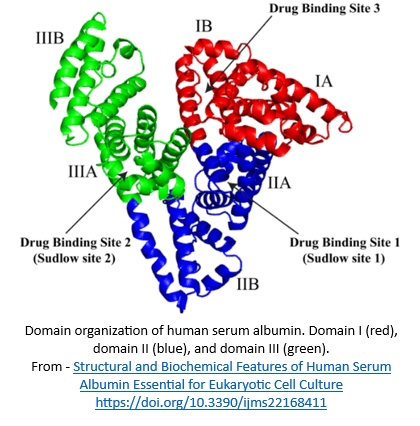
The albumin structure is a single chain polypeptide (amino acids) chain. It comprises 3 domains (I, II, III), and each domain contains 2 subdomains (A, B). There is minimal contact between domains I + III, and all primary contact is through domain II. The subdomains contain a variety of amino acid-based binding sites.
The structure is very open and vaguely based on a heart or V shape. An open structure means it can carry compounds with a variety of shapes and sizes. A range of factors, endogenous and/or exogenous, can alter albumin’s structure, resulting in altered functionality and effectiveness. The ultimate outcomes of modification to albumin’s structure are both altered metabolic processes, and altered therapeutic benefit of interventions.
Some analogies about albumin. Albumin has size constraints like a cargo plane and cannot add extra trailers like a road train. It has defined zoned areas with limited overlap like a cargo boat (wheelhouse, kitchen/galley, crew quarters, engine room, cargo). Its route is defined similarly to a train.
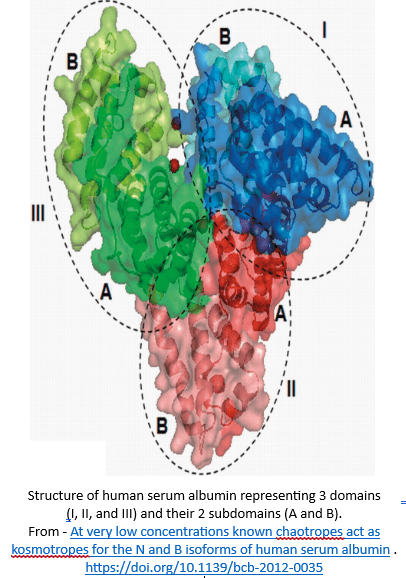
Binding sites
The albumin structure is designed to accommodate multiple binding sites and with some flexibility for compound shape and size.
Binding between compounds and albumin is determined by the number and availability of binding sites for each compound, and albumin’s affinity for the compound.
Identified binding sites include -
- Sudlow site I. Is located in subdomain IIA. Compounds include bulky heterocyclic molecules such as dicarboxylic acids. Site I shows poor stereoselectivity, which might also be due to the flexibility of this site.
- Sudlow site II. Aka FA3-4 site, and is located in subdomain IIIA. Compounds include aromatic carboxylates with an extended conformation. Site II often shows stereoselectivity and therefore is less flexible.
- Binding site 3. Aka FA1 site and is located in subdomain IB.
- FA5 site. Located in subdomain IIIB.
- Subdomains IA + IIB. The evidence is sparse to non-existent with regard to any compounds associated with these subdomains.
There seem to be 3 key areas for albumin-based drug-nutrient interactions –
- structural changes altering access to binding sites, especially nutrient access. Note - drug-induced structural changes impacting drug effects are much more likely to be investigated and known;
- competition between drugs and nutrients for shared binding sites;
- inhibited access to the carrier. A known example is aspirin’s inhibition of vitamin C access to albumin (MedNut Mail Aspirin-vitamin C interactions).
I have allocated these mostly unknown, key interactions to the “why don’t we know this already” basket.
Clinical Concerns
The “salting” of drugs with nutrients to utilise albumin as their distribution vehicle is a potential source of nutrient toxicity. Consequently, nutrient content in each drug dose should be included in the Product Information documents. As these are “new” techniques, the Regulators are yet to initiate any decrees – let’s hope they do so and soon.
There is no regulatory requirement for Product Information documents to include –
- the impacts of pharmaceuticals and nutrients the albumin structure,
- the specific subdomains and their specific binding sites for each pharmaceutical product.
Clinical Questions
What actions will you initiate as you a review a person whose prescribed medications profile includes one or more drugs that utilize albumin as a carrier, will you -
- recommend checking inflammatory markers such as TNF-α and IL-6, and B12 status (because it also impacts TNF-α status) if hypoalbuminaemic?
Conclusions
Albumin is the primary carrier in the body’s distribution system. The evidence for albumin-based drug-nutrient interactions is remarkably limited.
Bibliography
Kumar, D., Al-Anazi, KM., Farah, MA. & Ali, A. 2025. Role of Ascorbic Acid and Pyridoxal-5-Phosphate in the Prevention of Glucose-Induced Damage of Protein and DNA. Natural Product Communications 20(2). doi:10.1177/1934578X251319388
Garapati, K., Jain, A., Madden, BJ., Mun, DG., Sharma, J., Budhraja, R. & Pandey, A. 2024. Defining albumin as a glycoprotein with multiple N-linked glycosylation sites. Journal of Translational Medicine 22(1):454. https://link.springer.com/article/10.1186/s12967-024-05000-5. PMID: 38741158; PMCID: PMC11090807.
Jalali, E., Sargolzaei, J. & Rajabi, P. 2024. Mechanistic insights into the interaction of anxiolytic drugs with human serum albumin in a ternary system utilizing spectroscopic and molecular modeling approaches. Scientific Reports 14(1):25480. https://doi.org/10.1038/s41598-024-76544-1. PMID: 39461990; PMCID: PMC11513042.
Yoo, SY., Mun, YH., Kang, NW., Koo, JM., Lee, DH., Yoo, JH., Lee, SM., Koh, S., Park, JC., Kim, T., Shin, EK., Lee, HS., Sim, J., Kang, KW., Kim, SK., Cho, CW., Kim, MG., Kim, DD. & Lee, JY. 2022. Enhancement of the therapeutic efficacy of the MAP regimen using thiamine pyrophosphate-decorated albumin nanoclusters in osteosarcoma treatment. Bioengineering & Translational Medicine 8(6):e10472. https://doi.org/10.1002/btm2.10472. PMID: 38023714; PMCID: PMC10658614.
Belinskaia, DA., Voronina, PA., Shmurak, VI., Jenkins, RO. & Goncharov, NV. 2021. Serum Albumin in Health and Disease: Esterase, Antioxidant, Transporting and Signaling Properties. International Journal of Molecular Science 22(19):10318. https://doi.org/10.3390/ijms221910318. PMID: 34638659; PMCID: PMC8508759.
De Simone, G., di Masi, A. & Ascenzi, P. 2021. Serum Albumin: A Multifaced Enzyme. International Journal of Molecular Science 22:10086. https://doi.org/10.3390/ijms221810086
Iqbal, S., Alam, MM. & Naseem, I. 2016. Vitamin D prevents glycation of proteins: an in vitro study. FEBS Letters 590:2725-2736. https://doi.org/10.1002/1873-3468.12278
Cite: Coleman, Y. 2025. About Albumin. MedNut Mail https://medicationsandnutrition.com/about-albumin/ Accessed (date)
About Albumin

